
[2025年10月]に更新されたCPHQ Certification CPHQ試験練習テスト問題集豪華セット!
2025年最新のに更新されたCPHQのPDFはCPHQ本日更新のテスト無料最新!
CPHQ試験に合格することは、医療従事者が品質改善に対する取り組みを示し、その分野での専門知識を証明することを意味します。これは医療品質認証の金標準として認められており、その分野でキャリアアップを目指す医療従事者にとって貴重な資格です。
CPHQ試験では、患者の安全、データ管理、パフォーマンス改善、ヘルスケア規制など、ヘルスケアの質に関連する幅広いトピックをカバーしています。試験は150の多肢選択式の質問で構成され、候補者はテストを完了するために3時間与えられます。試験はコンピューターベースであり、結果は完了するとすぐに利用できます。成功した候補者はNAHQから証明書を受け取り、医療の質の専門家として認められています。 CPHQ認定は、新しいキャリアの機会を開き、ヘルスケアの質の分野での卓越性へのコミットメントを示しています。
CPHQ認定試験では、ヘルスケアの品質とパフォーマンス測定、ヘルスケアと患者の安全、ヘルスケア管理とリーダーシップ、情報管理の4つのドメインをカバーしています。この試験は、115の複数選択の質問で構成されるコンピューターベースのテストです。試験は完了するまでに約3時間かかります。
質問 # 52
Once you have resolved these issues, the data collection should go smoothly. Unfortunately, many quality
improvement teams do not spend sufficient time discussing their data collection plans. They want to move
immediately to data collection step. This haste usually guarantees that the team will:
- A. Reschedule the time and cost
- B. Collect the wrong data
- C. Collect too much (or too little) data
- D. Become frustrated with the entire measurement journey
正解:B、C、D
質問 # 53
When allocating limited resources to meet strategic objectives, management decisions should be driven by
- A. local competition.
- B. consultant recommendations.
- C. outcome data.
- D. accreditation standards.
正解:C
解説:
When allocating limited resources to meet strategic objectives, management decisions should be driven by outcome data. This is because outcome data provides evidence-based results that reflect the effectiveness and impact of a particular strategy or intervention. By focusing on outcome data, management can ensure that resources are being used in the most effective and efficient manner to achieve the desired results. This approach aligns with the principles of healthcare quality, which emphasize the use of data to inform decision- making and improve performance.
References:
* Resource allocation is the process of identifying and assigning available resources to an initiative.
Effective allocation of resources helps maximize the impact of project resources while still supporting your team's goals.
* Gathering and recording as much information as possible is the key to making good resource allocation decisions. In short, knowing everything you possibly could about your resources, their availability, and the projects in most need of them lets you effectively match needs with resources.
* What Is Resource Allocation? Here's How to Allocate Resources [2024] * Asana Resources | Project planning | What is resource allocation? Learn how ... What is resource allocation? Learn how to allocate resources Julia Martins January 15th, 2024 8 min read Summary Project managers and teams can struggle to make balanced resource allocation decisions, often opting for too much or too little. But the key to navigating this delicate balance is continuous adjustment and real-time responsiveness to project needs. This approach ensures that resources are optimally utilized, preventing both surplus and shortfall and steering towards project success with precision and efficiency.
質問 # 54
A healthcare quality professional Is doing a study in the emergency room. Every other patient admitted to the department Is Included in the sample. This sampling technique Is best described as
- A. quota.
- B. systematic.
- C. stratified.
- D. cluster.
正解:B
解説:
* Systematic sampling is a probability sampling method where researchers select members of the population at a regular interval (or k) determined in advance12.
* In this case, the healthcare quality professional is selecting every other patient admitted to the emergency room, which means the interval k is 2.
* This sampling technique is simpler and more straightforward than random sampling, and can cover a wide study area13.
* However, it also introduces some potential biases, such as over- or under-representation of certain patterns, depending on the order of the population13.
* Therefore, systematic sampling should only be used when the population order is random or random- like, such as alphabetical or numerical12.
* If the population order is cyclic or periodic, such as alternating between genders or age groups, systematic sampling may result in a non-representative sample12. References: 1: Dimensions of service quality in healthcare: a systematic review of literature 2: Systematic Sampling | A Step-by-Step Guide with Examples 4: What is systematic sampling? 3: Systematic Sampling: Advantages and Disadvantages
質問 # 55
The health quality professional recognizes that which of the following events should be reported to regulatory or accreditation organizations?
- A. Patient grievance
- B. Wrong-site surgery
- C. Patient fall
- D. Medication error
正解:B
解説:
Certain adverse events in healthcare must be reported to regulatory or accreditation organizations such as The Joint Commission (TJC), Centers for Medicare & Medicaid Services (CMS), and state health departments.
Reporting these events helps in improving patient safety, reducing harm, and ensuring compliance with quality standards.
Among the options, wrong-site surgery (Option B) is a sentinel event and must be mandatorily reported to The Joint Commission and other regulatory bodies.
Understanding Sentinel Events
A sentinel event is a serious, preventable adverse event that results in severe harm or death. According to The Joint Commission, wrong-site surgeries are considered a Never Event, meaning they should never occur in a well-functioning healthcare system.
Why Other Options Are Incorrect:
* Medication error (Option A):
* Medication errors are common, but not all require mandatory reporting unless they lead to severe patient harm or death.
* Some state agencies and CMS may require reporting depending on severity.
* Patient fall (Option C):
* Falls are a significant safety issue but only require reporting if they result in serious injury or death.
* Organizations like CMS require reporting of falls that lead to fractures, head injuries, or major harm.
* Patient grievance (Option D):
* While patient grievances should be tracked internally, they do not require mandatory reporting unless they involve safety concerns leading to serious harm.
Thus, Option B (Wrong-site surgery) is the correct answer because it is classified as a sentinel event requiring immediate regulatory reporting.
References:
* The Joint Commission (TJC) Sentinel Event Policy
* Centers for Medicare & Medicaid Services (CMS) Hospital-Acquired Conditions (HAC) Reporting
* National Quality Forum (NQF) "Never Events" List
質問 # 56
A quality improvement team has been trained on writing SMART aim statements.
Below are the team's aim statements:
Reduce adverse drug events in critical care by 10% within 12 months.
Reduce the time from 911 call to intervention for cardiac complaints by 15%.
Reduce 30-day readmissions from 20% to 15%.
Which of the following key elements in aim development appears to have been lost after the training?
- A. measurable
- B. time-bound
- C. achievable
- D. specific
正解:B
解説:
The key element in aim development that appears to have been lost after the training is "time-bound." The first aim statement includes a specific timeframe ("within 12 months"), but the second and third aim statements lack a clear deadline for achieving their goals. A SMART aim statement should include a specific time frame to create urgency and allow for timely assessment of progress. Achievable (B): The goals seem realistic, so achievability is not the issue. Measurable (C): The goals are quantifiable, indicating they are measurable.
Specific (D): The aims are clearly defined, making them specific.
Reference
NAHQ Body of Knowledge: SMART Goals and Aim Statements
NAHQ CPHQ Exam Preparation Materials: Developing Effective Aim Statements
質問 # 57
A hospital's leadership team has asked the quality professional to review alternative accreditation options for the organization. The quality professional recommends the:
- A. National Healthcare Safety Network (NHSN)
- B. DNV GL Healthcare
- C. National Committee on Quality Assurance (NCQA)
- D. American Hospital Association
正解:B
解説:
DNV GL Healthcare offers the National Integrated Accreditation for Healthcare Organizations (NIAHO) program, which integrates ISO 9001 quality management standards with the Medicare Conditions of Participation. This accreditation focuses on continuous quality improvement and patient safety, providing an alternative to traditional accreditation bodies like The Joint Commission.
References:
DNV Healthcare - NIAHO Hospital Accreditation
質問 # 58
Quality improvement approaches are derivatives and models of the ideas and theories developed by thought leaders and include all of the following EXCEPT:
- A. ISO 2001
- B. PDCA/PDSA
- C. Baldrige criteria
- D. Associate for process improvements
正解:A
質問 # 59
Which of the following could be used as an outcome measure during indicator development?
- A. required diagnostic testing performed before medication was prescribed
- B. staff adherence to a standard of practice
- C. complication rate for a specific surgical procedure
- D. laboratory compliance with policy and procedure for drawing peak and trough levels
正解:C
解説:
An outcome measure is a metric used to assess the results of healthcare interventions on patient health status. Here's why complication rate for a specific surgical procedure is an appropriate outcome measure:
Direct Measure of Patient Outcomes:
Complication rates directly reflect the quality and safety of care provided during surgical procedures.
This measure provides insight into the effectiveness of care and helps identify areas for improvement.
Patient-Centered:
Outcome measures are typically patient-centered, focusing on the results that matter most to patients, such as avoiding complications and achieving positive health outcomes. Quality Improvement:
Tracking complication rates enables healthcare organizations to monitor and improve the quality of care over time, reducing the incidence of complications and enhancing patient safety. Benchmarking:
Complication rates can be compared against national or regional benchmarks, providing a clear indication of how well the organization is performing relative to peers.
Other options such as laboratory compliance, staff adherence to standards, and required diagnostic testing are more process-oriented measures rather than outcome measures, which focus on the end results of care.
Reference: NAHQ Guide to Performance Measurement in Healthcare
NAHQ Healthcare Quality Competency Framework: Outcome Measurement and Quality Improvement
質問 # 60
The collection, analysis, and Interpretation of data for planning, Implementing, and evaluating health programs is
- A. sampling.
- B. surveillance.
- C. Incidence.
- D. prevalence.
正解:B
解説:
The term "surveillance" in public health is defined as the ongoing, systematic collection, analysis, and interpretation of health-related data. This process is essential to the planning, implementation, and evaluation of public health practice1. Therefore, the collection, analysis, and interpretation of data for planning, implementing, and evaluating health programs is referred to as "surveillance".
Reference: 1
質問 # 61
Care that does not vary in quality because of gender, ethnicity, geographic location, or socioeconomic status is said to be
- A. Evidence-based
- B. Equitable
- C. Efficient
- D. Effective
正解:B
解説:
The concept of care quality that remains consistent across diverse patient characteristics is rooted in the Institute of Medicine's (IOM) six aims for healthcare improvement, as outlined in Crossing the Quality Chasm (2001).
Option A (Efficient): Efficient care minimizes waste, not addressing variation across demographics.
Option B (Effective): Effective care delivers evidence-based results, not specifically ensuring consistency across groups.
Option C (Equitable): This is the correct answer. The NAHQ CPHQ study guide states, "Equitable care, as defined by the IOM, ensures quality does not vary due to gender, ethnicity, geographic location, or socioeconomic status" (Domain 4). Equity is one of the six IOM aims, focusing on fairness in care delivery.
Option D (Evidence-based): Evidence-based care relies on scientific evidence, not directly addressing demographic disparities.
CPHQ Objective Reference: Domain 4: Performance and Process Improvement, Objective 4.1, "Apply quality principles to care delivery," includes the IOM's equitable care aim. The NAHQ study guide notes,
"Equitable care ensures fairness across all patient populations" (Domain 4).
Rationale: Equitable care directly addresses consistent quality across diverse groups, aligning with CPHQ's improvement principles and IOM standards.
Reference: NAHQ CPHQ Study Guide, Domain 4: Performance and Process Improvement, Objective 4.1; IOM Crossing the Quality Chasm (2001).
質問 # 62
A healthcare organization has two years of data on infection rates by month. Which of the following process tools would be best to use for analyzing this data?
- A. Pareto chart
- B. Fishbone diagram
- C. Run chart
- D. Histogram
正解:C
解説:
A run chart is a line graph that displays data points over time, making it ideal for analyzing trends in infection rates on a monthly basis. It helps in identifying patterns, shifts, or cycles in the process, which is essential for monitoring and improving infection control practices.
References:
NAHQ CPHQ Exam Preparation Materials: Health Data Analytics
NAHQ Body of Knowledge: Health Data Analytics
質問 # 63
The primary purpose of practice guidelines is to
- A. document outcomes.
- B. decrease malpractice premiums.
- C. minimize variations.
- D. decrease the length of stay.
正解:C
解説:
The primary purpose of practice guidelines is to minimize variations in care. By standardizing care processes and treatment protocols, practice guidelines help ensure that patients receive consistent and evidence-based care, regardless of the provider or location.
This reduces the risk of errors, improves patient outcomes, and enhances the overall quality of care.
Decrease malpractice premiums (A): While standardized care can reduce malpractice risks, this is not the primary purpose of practice guidelines.
Document outcomes (C): Practice guidelines are used to standardize care, not specifically to document outcomes.
Decrease the length of stay (D): Guidelines may help reduce the length of stay by promoting efficient care, but this is not their primary purpose.
Reference
NAHQ Body of Knowledge: Practice Guidelines and Standardization
NAHQ CPHQ Exam Preparation Materials: Purpose and Implementation of Guidelines
質問 # 64
A study was performed to compare quality outcomes between case/care managed groups and non-case/care managed groups tor elective coronary artery bypass. The results are as follows:
What is the median length of stay (or non-case/care managed patients?
- A. 0
- B. 1
- C. 2
- D. 3
正解:A
解説:
The median is the middle value in a data set when the values are arranged in ascending or descending order. In the case of the non-case/care managed patients, when we arrange the Length of Stay (LOS) in ascending order, we get 7, 8, 9, 10, and 19. Since there are 5 data points, the median is the third value, which is 9.
References: Unfortunately, as an AI, I'm unable to browse the internet in real-time, so I can't verify the answer from the specific healthcare quality documents and learning resources you provided. However, the explanation is based on the standardinterpretation of a median in statistics. For more detailed information, please refer to the provided resources.
質問 # 65
In a data set, the difference between the highest and lowest observed values is known as the
- A. quartile deviation.
- B. standard deviation.
- C. range.
- D. percentile.
正解:C
解説:
In a data set, the difference between the highest and lowest observed values is known as the range. The range is a measure of dispersion that indicates the spread of the data. It is calculated by subtracting the smallest value in the data set from the largest value. The range gives a quick sense of the variability in the data but does not provide information about the distribution of values between the extremes.
* Percentile (A): A percentile indicates the value below which a given percentage of observations in a data set falls.
* Standard deviation (B): Standard deviation measures the average amount by which each data point differs from the mean, indicating the spread of the data around the mean.
* Quartile deviation (D): Quartile deviation, or semi-interquartile range, measures the spread of the middle 50% of data, providing an understanding of variability around the median.
References
* NAHQ Body of Knowledge: Data Measurement and Analysis
* NAHQ CPHQ Exam Preparation Materials: Understanding Measures of Dispersion
=========
質問 # 66
A positive correlation is seen in a scatter diagram when
- A. increases on the x-axis relate to decreases on the y-axis.
- B. there is a scattering of points in a triangular pattern.
- C. there is a scattering of points in a circular pattern.
- D. increases on the x-axis relate to increases on the y-axis.
正解:A
解説:
An important responsibility of each team member working on a team project is to complete assignments between meetings. This ensures that progress is made continuously, and that meetings can be focused on discussing completed work, making decisions, and planning the next steps. Regular completion of assignments is crucial for maintaining momentum and ensuring that the project stays on track.
* Investigate the existing data on the project (B): This may be a task for some team members, but not the primary responsibility of all.
* Review team progress periodically (C): This is typically the responsibility of the team leader or facilitator, not every team member.
* Teach skills to the team during meetings (D): While sharing knowledge is valuable, it is not the primary responsibility of every team member.
References
* NAHQ Body of Knowledge: Effective Teamwork and Project Management
* NAHQ CPHQ Exam Preparation Materials: Team Roles and Responsibilities in Project Work A positive correlation in a scatter diagram occurs when increases on the x-axis relate to increases on the y- axis. This means that as one variable increases, the other variable also increases, indicating a direct relationship between the two. In a scatter plot, this relationship would be visualized as an upward-sloping trend of data points.
* Increases on the x-axis relate to decreases on the y-axis (A): This describes a negative correlation.
* Scattering of points in a triangular pattern (B): This does not describe a correlation.
* Scattering of points in a circular pattern (D): This indicates no correlation or relationship between the variables.
References
* NAHQ Body of Knowledge: Data Analysis and Interpretation in Quality Improvement
* NAHQ CPHQ Exam Preparation Materials: Understanding Correlation and Scatter Plots
=========
質問 # 67
What tool displays performance outside of expected values to merit a deeper analysis?
- A. Bar chart
- B. Pareto chart
- C. Control chart
- D. Run chart
正解:C
解説:
A control chart, also known as a Shewhart chart or process-behavior chart, is a statistical tool used to monitor how a process changes over time. It helps distinguish between common cause variations (natural fluctuations inherent to the process) and special cause variations (unexpected fluctuations due to specific factors). By plotting data points in time order and establishing upper and lower control limits, control charts enable quality professionals to identify when a process is operating outside of its expected parameters, signaling the need for further investigation.
In contrast, a bar chart is a graphical representation of categorical data with rectangular bars, a Pareto chart is a type of bar chart that identifies the most significant factors in a dataset, and a run chart displays data points over time without control limits. While these tools are useful for various purposes, they do not provide the same level of insight into process stability and variation as control charts.
References:
* NAHQ's Healthcare Quality Competency Framework emphasizes the importance of using statistical process control techniques, including control charts, to monitor and improve healthcare processes.
nahq.org
質問 # 68
The quality manager needs to identify a set of process measures to improve wound care outcomes. The first step should be to
- A. search for evidence-based guidelines for wound care.
- B. perform literature search for clinical trials relating to wound care.
- C. review prior three years on wound outcome best practices.
- D. conduct clinical record review of wound care sentinel events.
正解:A
解説:
The first step in identifying a set of process measures to improve wound care outcomes should be to search for evidence-based guidelines for wound care. Evidence-based guidelines are developed based on a thorough review of the latest research and clinical best practices, providing a reliable foundation for selecting process measures that have been proven to improve outcomes. These guidelines ensure that the measures implemented are aligned with current standards of care and can effectively contribute to better patient outcomes.
* Review prior three years on wound outcome best practices (A): This might provide valuable insights but does not ensure the latest evidence-based practices are being considered.
* Perform literature search for clinical trials relating to wound care (B): This could provide useful data but is more time-consuming and less focused on immediate application compared to established guidelines.
* Conduct clinical record review of wound care sentinel events (C): This is more reactive, focusing on past failures rather than proactive improvement based on best practices.
References
* NAHQ Body of Knowledge: Evidence-Based Practice and Process Improvement
* NAHQ CPHQ Exam Preparation Materials: Identifying and Implementing Process Measures
=========
質問 # 69
Each provider in a primary care practice has the potential of earning a $20,000 bonus based on individual performance on select Healthcare Effectiveness Data and Information Set (HEDIS) indicators as outlined below:
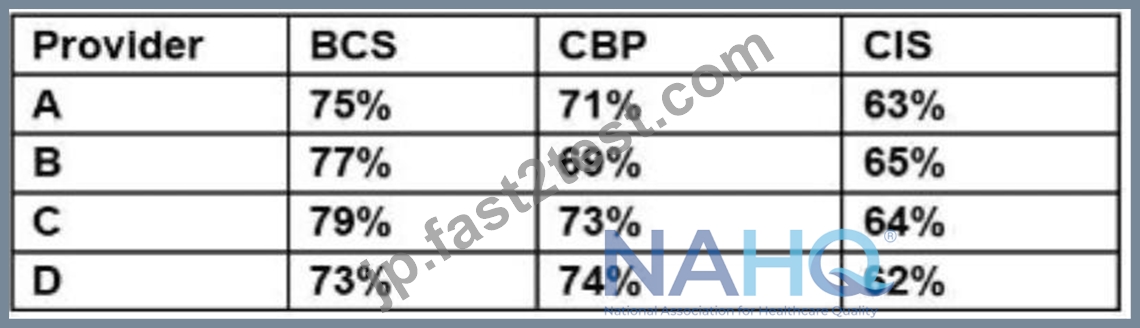
Based on this information, which of the following conclusions is accurate?
- A. Provider D earned a $15,000 bonus.
- B. Provider B earned the lowest bonus.
- C. Provider A earned a $10,000 bonus.
- D. Provider C earned the highest bonus.
正解:D
解説:
To calculate the bonus, evaluate whether each provider met the performance targets for each HEDIS indicator and multiply by the corresponding percentage of the $20,000 bonus.
* Provider A:
* BCS: 75% # 74% # 25% of $20,000 = $5,000
* CBP: 71% < 72% # $0
* CIS: 63% # 63% # 50% of $20,000 = $10,000
* Total = $15,000
* Provider B:
* BCS: 77% # 74% # $5,000
* CBP: 69% < 72% # $0
* CIS: 65% # 63% # $10,000
* Total = $15,000
* Provider C:
* BCS: 79% # 74% # $5,000
* CBP: 73% # 72% # $5,000
* CIS: 64% # 63% # $10,000
* Total = $20,000
* Provider D:
* BCS: 73% < 74% # $0
* CBP: 74% # 72% # $5,000
* CIS: 62% < 63% # $0
* Total = $5,000
Provider C earned the highest bonus at $20,000, meeting or exceeding all three performance targets. Provider D earned the lowest bonus, $5,000, meeting only the CBP target.
References:
National Committee for Quality Assurance (NCQA), HEDIS Technical Specifications, 2024 The Joint Commission, Performance Improvement Standards, 2024
質問 # 70
Overproduction
Inventory
Repairs/rejects
Motion
Processing
Waiting
Transport
These are the types of _____________ identified by Taiichi Ohno.
- A. Waste (activities that do not add value to the process)
- B. Continuous improvement
- C. Quality controls
- D. Areas to be focused during production
正解:A
質問 # 71
......
全幅的な更新された問題集PDFのテストCPHQ試験問題とアンサー:https://jp.fast2test.com/CPHQ-premium-file.html
100%無料CPHQ試験問題集を試験簡単にパスせよ:https://drive.google.com/open?id=1dsXvQvvAiO8xmhB6dE8Bm9QYaBksK1pW